
Stepping into freezing water triggers an ancient survival reflex that reshapes human physiology within seconds. While social media often frames deliberate cold immersion as an exercise in mental grit, cold plunge science reveals a sophisticated neurochemical and metabolic response that extends far beyond subjective perception. Exposure to cold water forces the autonomic nervous system, endocrine glands, and vascular networks into rapid coordination to defend core body temperature.
Understanding cold plunge science enables individuals to bypass exaggerated marketing claims and design protocols grounded in rigorous human physiology. The biological reaction depends entirely on exact temperature exposure, immersion timing, and mechanical factors like water movement. When applied with physiological precision, cold water immersion serves as a targeted stimulus that interacts with systemic inflammation, neurochemistry, and energetic adaptation, though individual responses vary considerably.
Sudden contact with cold water triggers cutaneous thermal receptors that instantly alert the central nervous system. This peripheral shock travels along unmyelinated C-fibers and myelinated A-delta fibers through the spinal cord and ascending pathways to thermoregulatory brain circuits, initiating an immediate systemic stress response.
When cold water envelops the torso, the sympathetic nervous system releases norepinephrine into the bloodstream. A frequently cited small study measured plasma norepinephrine and dopamine concentrations in participants after a full hour of head-out immersion in water at 14°C, finding increases of roughly 500 percent and 250 percent respectively. These figures describe hormone levels circulating in the blood, not direct measurements of neurotransmitter activity inside the brain, and they come from a prolonged one-hour exposure rather than a brief plunge of a few minutes.
Because that research measured a full hour of immersion, it does not establish how quickly these changes appear during a short plunge or how long any elevation actually lasts afterward. Some people report extended focus and a steadier mood following cold exposure, and plasma catecholamine shifts are a plausible contributor, but the precise timeline for a typical two-to-five-minute session has not been established in that study.
The initial plunge causes an abrupt shift into sympathetic dominance, characterized by gasping respiration and a brief tachycardia. Survival instinct urges an immediate exit, yet maintaining controlled, diaphragmatic breathing can help down-regulate this panic response. Consciously calming the respiratory rate during thermal shock is one way practitioners describe retaining more deliberate control over an otherwise automatic reflex.
Once immersion ends and shivering subsides, some individuals experience a parasympathetic rebound, including a slower heart rate and shifts in heart rate variability measures such as RMSSD. These post-exposure responses appear to be context-dependent rather than universal, and they vary by individual, water temperature, and immersion duration. Whether repeated cold exposure produces a lasting change in baseline autonomic flexibility is not something this article can confirm, and readers should treat that possibility as an open question rather than a guaranteed outcome.
Systemic hypothermic stress prompts cells to synthesize specialized molecular chaperones known as cold shock proteins, primarily RNA-binding motif protein 3, or RBM3. Most of what is known about RBM3’s role in preserving synaptic density and protecting dendrites comes from laboratory and animal research conducted under controlled hypothermic conditions. This body of work supports RBM3 as a research hypothesis worth watching, but it does not demonstrate that an ordinary cold plunge raises RBM3 levels in human neural tissue or protects a person’s dendrites in practice.
Deliberate cold exposure is sometimes framed as a hormetic challenge, meaning a brief, sub-lethal stressor that may prompt the body’s defenses to respond more robustly than the stressor itself would otherwise demand. This framework is a useful way to think about controlled stress exposure, but claims that cold plunging reliably builds measurable antioxidant capacity or long-term resilience in humans remain unproven and should be read as a hypothesis rather than an established benefit.
Human energy expenditure during cold exposure undergoes a fundamental shift as the body defends its core internal temperature against convective heat transfer. Water is a far more effective conductor of thermal energy than air at the same temperature, so immersion generally increases heat transfer away from the skin compared with simply standing in cold air, though the actual rate depends on water movement, the temperature gradient, and other conditions rather than a single fixed multiple.

White adipose tissue functions primarily as passive energy storage, accumulating lipids in single large droplets. In contrast, brown adipose tissue contains dense clusters of iron-rich mitochondria and smaller lipid droplets, structured specifically to burn biochemical substrate directly into thermal energy rather than generating cellular ATP.
Cold exposure activates the sympathetic nervous system, which releases norepinephrine onto brown adipose tissue. This signaling acts mainly through beta-adrenergic receptors on brown adipocytes, which in turn activates uncoupling protein 1 located within the inner mitochondrial membrane. By short-circuiting the proton electrochemical gradient, uncoupling protein 1 permits cellular respiration to dissipate energy largely as heat, a mechanism that is well documented in brown fat physiology, though the magnitude of its contribution to daily caloric expenditure in adult humans is still debated among researchers.
Thermogenesis takes two distinct pathways during cold water exposure: non-shivering thermogenesis driven by brown fat activation, and involuntary shivering driven by rapid, oscillatory muscle contractions. Shivering consumes glycogen reserves rapidly to produce immediate convective heat, while non-shivering thermogenesis is the pathway more closely associated with brown fat activity.
Physiological researcher Susanna Søberg studied experienced winter swimmers and observed that this group accumulated roughly 11 minutes of cold water immersion per week on average, divided across several short sessions. That figure describes a pattern observed within a specific, cold-adapted cohort; it was not established as a minimum effective dose or a validated threshold for triggering metabolic-rate improvements or brown fat recruitment in a general population. Readers should treat the 11-minute figure as descriptive of that study population rather than as a prescription.
Some clinical trials report changes in insulin sensitivity among individuals with metabolic dysfunction following structured cold acclimation, though findings vary across study populations and are not consistent enough to support a firm general claim. The proposed mechanism, that brown fat activity draws glucose and other fuel substrates out of circulation, is a reasonable hypothesis grounded in brown fat physiology, but its practical relevance to someone taking occasional cold plunges has not been clearly established and is best treated as a proposed pathway rather than a confirmed outcome.
Cold exposure also causes cutaneous arterioles and other small vessels in the skin to constrict, redirecting blood flow toward deep vital organs, while skin blood flow increases again once warming begins. This vasoconstriction-dilation cycle is well documented as an acute physiological response, though the rewarming phase should not be assumed to match the specific clinical pattern known as reactive hyperemia unless measured directly. Whether repeated cycles produce a durable improvement in endothelial flexibility or peripheral perfusion over time is a plausible but separate question that the available evidence does not settle here.
| Physiological Parameter | Baseline State | Acute Cold Exposure | Post-Plunge Response |
|---|---|---|---|
| Plasma Norepinephrine | Baseline (1.5–2.5 nmol/L) | Reported increase of roughly 500% after one hour at 14°C in one study | Gradually returns toward baseline; exact timeline not established for brief plunges |
| Plasma Dopamine | Stable steady-state | Reported increase of roughly 250% after one hour at 14°C in one study | Duration of elevation not established for brief plunges |
| Primary Thermogenic Mode | Basal mitochondrial rate | Mix of shivering and non-shivering thermogenesis | Continued rewarming, partly via brown fat activity |
| Cutaneous Vascular Tone | Resting compliance | Constriction of cutaneous arterioles and small vessels | Increased skin blood flow as vessels relax |
| Primary Autonomic Driver | Sympathovagal balance | Acute sympathetic surge | Possible vagal rebound, varies by individual |
Athletes frequently turn to cold water immersion to diminish soreness and accelerate readiness for upcoming competition. However, scientific literature points to a tradeoff worth understanding between acute recovery and long-term skeletal muscle adaptation.
Strenuous or unaccustomed exercise, particularly movements with a heavy eccentric loading component, can cause muscle damage and trigger local inflammatory responses. The mechanisms behind delayed-onset muscle soreness are multifactorial and not fully settled, but swelling and the sensitization of nearby nerve endings are thought to contribute to the discomfort. Cold-water immersion is widely reported to reduce perceived soreness in this context, and reduced local blood flow and limited swelling are commonly proposed mechanisms behind that effect, though the precise pathways and their relative contributions are not fully settled.
Hypothermia is also known to slow sensory nerve conduction velocity across peripheral nerve tracts, which may contribute to a local analgesic-like effect. Subjective perception of physical recovery often improves, allowing competitive athletes facing multi-round tournaments or short rest turnarounds to perform without being limited by severe muscular pain.
While suppressing inflammation aids short-term recovery, acute inflammation serves as an essential biochemical trigger for muscular hypertrophy and strength gains. Trials led by exercise physiologist Llion Roberts found that regular, immediate cold water immersion after resistance training was associated with reduced phosphorylation of key downstream targets in the mammalian target of rapamycin complex 1 (mTORC1) pathway, including p70S6 kinase, compared with active recovery.
That same research line reported that athletes who consistently plunged immediately after resistance training sessions experienced smaller muscle fiber cross-sectional area increases and reduced strength gains over the training block compared with athletes using active recovery methods. This finding supports caution around making immediate post-lifting cold immersion a habitual practice, though it does not by itself define a precise safe waiting period.
Rather than following a single fixed schedule, athletes and coaches generally weigh timing decisions against their current training priority:
If the immediate priority is competing again soon or managing soreness between tournament rounds, cold immersion shortly after exercise can ease perceived discomfort, with the understanding that doing this habitually after resistance training may come at some cost to long-term strength and size gains.
If the immediate priority is maximizing muscle growth or strength from a specific resistance training block, the available research supports avoiding routine immediate post-lifting cold immersion, since regular use in that window has been linked to blunted hypertrophy signaling. The evidence does not define one precise safe interval, so many coaches build in a longer gap as a conservative buffer rather than relying on an exact cutoff.
If the priority is general wellness, mental readiness, or an endurance-focused training phase rather than hypertrophy, the tradeoff described above is less relevant, and timing can be chosen more flexibly around personal preference and schedule.

Achieving consistent physiological outcomes demands reliable engineering. In controlled research settings, immersion variables are carefully managed, whereas improvised backyard tubs frequently fail to deliver reliable, repeatable conditions.
A stationary body resting in uncirculated water gradually warms the thin micro-layer of fluid immediately adjacent to the skin. This thermal boundary layer can insulate the cutaneous thermoreceptors to some degree, meaning the water in direct contact with skin may feel milder than the bulk water temperature suggests. The speed and extent of this effect depend heavily on the specific setup, water volume, and body position, so no single fixed timeframe applies universally across different tubs or barrels.
Active water circulation is one way to reduce this localized warming by continuously replacing the layer of water nearest the skin. Systems that move water help the cold water maintain more consistent contact with the epidermis throughout a session, though the resulting effect on comfort or physiological response will still vary with tub design and water flow rate.
Manual ice dumping tends to produce uneven, fluctuating water temperatures: the water starts out relatively mild, drops sharply once ice is added, and then gradually warms again as that ice melts. The exact numbers depend heavily on the volume of water in the tub and the quantity of ice used, so no single pair of before-and-after temperatures applies universally, but the underlying pattern of instability is a common practical complaint with manual ice-based setups.
For us at Ocean Future, aligning hardware design with cold plunge science means pairing dedicated refrigeration with structural insulation rather than relying on manual ice. The OF-CP01 cold plunge tub is built with a dedicated 1HP cold water chiller system, full PU thermal insulation, and a matching fitted tub cover, according to its product specifications. Constructed from Chinese white acrylic with dual hydrotherapy jets, the 2140 x 770 x 714 mm single-person basin is designed around these components to support more stable temperature control than manual ice-based setups, suited to indoor training rooms and outdoor patio installations alike.
Cold water systems still require attention to hygiene. Low temperatures can slow the replication of some common pathogens, but recirculating water left untreated can still support bacterial growth and biofilm over time, so cold alone is not a substitute for proper water treatment.
The OF-CP01 includes a built-in ozone generator and a filtration system as standard equipment, per its product specifications. These are included features intended to support water clarity and hygiene, rather than a standalone guarantee of sanitation; users should still follow the manufacturer’s recommended water-treatment and cleaning routine to keep the system running as intended.

Translating cold plunge science into everyday life requires realistic expectations rather than a single fixed protocol. More cold is not inherently better, and pushing exposure too far can lead to tissue injury, exhaustion, and other risks that outweigh any potential benefit.
Many published studies on cold water immersion use temperatures somewhere in the range of 10°C to 15°C (50°F to 59°F), and this range is often referenced as a common starting point rather than a strict universal standard. It is worth noting that cold shock responses, including the gasp reflex and a spike in heart rate, can occur even within this range, so the temperature alone does not guarantee a mild or predictable experience for every individual.
Colder water generally places greater physiological stress on the body, and the actual risk of discomfort or cold injury depends on exposure duration, water temperature, and individual factors such as body composition and prior cold adaptation rather than any single temperature cutoff. Rather than treating any specific range as a guarantee of safety, it is more realistic to start conservatively, pay attention to individual response, and adjust gradually rather than following a fixed number as a rule.
Session length and weekly frequency both matter, though the research does not point to one universally optimal combination:
Short sessions are common in published protocols, often in the range of a couple of minutes up to around five minutes, but this reflects typical study design rather than a hard ceiling or floor that applies to everyone.
Some researchers, including Søberg’s work with winter swimmers, have observed roughly 11 minutes of weekly cumulative exposure in that specific, cold-adapted group, though this is a descriptive observation rather than a prescribed weekly target for the general public.
Consistency across multiple shorter sessions is generally considered a reasonable approach by practitioners, though the available evidence does not establish that this pattern is definitively superior to other schedules for every goal.
Cold shock response presents an immediate safety consideration upon submersion. Rapid skin chilling can trigger an involuntary gasp reflex followed by rapid breathing; if the head goes underwater during this reflex, water aspiration becomes a real risk. Entering feet first, keeping the head above water, and focusing on slow, controlled breathing are practical ways to regain composure quickly.
After leaving the water, core body temperature can continue to drop for a period of time, a phenomenon generally referred to as afterdrop. The exact duration and magnitude vary from person to person and session to session, and the drop reflects ongoing heat exchange between the body’s core and its cooled peripheral tissues as circulation patterns shift back toward normal. A sensible approach is to dry off, dress in warm layers, and warm up gradually through gentle movement. Moving immediately into a very hot shower or sauna after a cold plunge is something some people prefer to avoid out of caution regarding sudden shifts in blood pressure, though individual tolerance differs and anyone with cardiovascular concerns should check with a doctor beforehand.
Deliberate cold exposure is associated with acute shifts in stress hormones and mood-related signaling that some people find energizing, but it should not be viewed as a standalone cure for clinical psychiatric conditions. It is better understood as a possible adjunctive habit alongside established clinical treatments, not a replacement for professional care.
Finishing with cold tends to sustain vasoconstriction for a period afterward, while finishing with heat promotes peripheral vasodilation and a more relaxed, sedated feeling. If your goal is alertness or an energizing effect, ending with cold is the more common choice; if your goal is relaxation or winding down before sleep, ending with heat tends to suit that purpose better.
Dedicated cold plunge tubs typically use a closed-loop refrigeration or chiller system that continuously cools water and circulates it back into the tub, maintaining a set target temperature without the need to add ice manually. The OF-CP01, for example, is built around a dedicated 1HP chiller system paired with insulation, according to its product specifications.
Full head submersion is not generally considered necessary to experience the main responses associated with cold water immersion. Immersing the body up to the shoulders or neck already engages the major systemic vascular beds and triggers a norepinephrine response, while keeping the head above water avoids added risks like ear discomfort and reduces the chance of an unexpected reaction to sudden cold on the face and scalp.
Individuals diagnosed with cardiovascular disease, arrhythmias, uncontrolled hypertension, or peripheral vascular conditions like Raynaud’s phenomenon should avoid deliberate cold water immersion unless specifically cleared by a medical doctor. The sudden rise in peripheral vascular resistance and blood pressure during cold shock can place meaningful stress on a compromised cardiovascular system.
Cold plunge science shows that deliberate cold water immersion is far more than an uncomfortable test of willpower, even though many of its proposed benefits remain under active study rather than firmly settled. It involves a real, measurable biological response, including shifts in circulating stress hormones, changes in blood vessel tone, and engagement of brown fat metabolism, alongside open questions about how durable or universal these effects truly are. By approaching exposure conservatively, paying attention to individual response, aligning timing with personal training goals, and maintaining clean, well-maintained equipment, practitioners can treat cold plunging as a reasonable, evidence-aware addition to a wellness routine rather than a guaranteed cure.

Guide explaining that no clinical standard exists for postpartum cold plunging, covering safety questions, clinician checks, and tub features.

Cold is a known Raynaud’s trigger and no safe plunge temperature exists, so see a clinician first; the OF-CP01 tub only aids monitoring.

This guide covers installing a cold plunge in a garage, addressing floor load, drainage, ventilation, electrical needs, and the OF-CP01 unit.

Cold plunge benefits for women vary by individual physiology, with research suggesting moderate temperatures and cycle-aware timing may support sustainable wellness practice.

Diarrhea after cold plunges has no proven cold-reflex cause, so track variables, keep water clean, and see a doctor if severe.

Guide turning cold plunge podcast science into safe routines, covering protocols, temperatures, and the OF-CP02 tub.

Cold plunge meditation pairs structured breathwork with cold immersion to train nervous system regulation, using a four-phase protocol and purpose-built tubs like the OF-CP01.

Alternating infrared sauna heat with cold plunge immersion offers a structured recovery protocol, though evidence and equipment choices like the OF-CP01 vary.

Cold plunging on your period is not proven to help cramps, so this guide covers safety, cycle science, cautions and an example routine.

Guide to choosing cold plunge or hot tub first: warm-then-cold suits daytime, cold-then-warm suits evenings, with safety cautions.

Current research does not support claims that cold water immersion treats, prevents, or improves liver disease or metabolic health in humans.

Cold plunge businesses require careful planning around equipment, sanitation, revenue models, and operational costs to succeed long-term.

Cold water immersion may reduce perceived muscle soreness and trigger acute stress responses, though optimal timing and long-term benefits remain unclear.

Cold water immersion activates brown adipose tissue through sympathetic nervous system signaling, triggering thermogenesis via the UCP1 protein in mitochondria-dense brown fat cells.

Cold plunging during breastfeeding lacks direct research, so mothers should consult providers on timing, hygiene, warming, and risks like nipple vasospasm.

Cold plunge books emphasize disciplined, gradual cold-exposure protocols, which modern tubs like the OF-CP01 help replicate through precise temperature and water control.

Neoprene cold plunge booties can improve foot comfort and grip during ice baths, though they don’t alter the body’s overall systemic cold response.

Peer-reviewed studies show no proven direct testosterone boost from cold plunging, though it may offer indirect recovery and alertness benefits.

Neoprene cold plunge socks use closed-cell foam and varied thicknesses to ease foot pain during icy water immersion without altering core cold-exposure benefits.

Engineered cold plunge barrels like the OF-CP01 use chillers, PU insulation, and ozone filtration for consistent, low-maintenance recovery sessions.

Cold water immersion triggers measurable hormonal, vascular, and metabolic changes, though many claimed benefits remain scientifically unsettled and timing-dependent.

Evidence on cold plunging during pregnancy is limited, so experts advise caution, individualized medical guidance, and gentler alternatives like foot soaks or compresses.

A structured cold plunge protocol covers water temperature, duration, breathing technique, and equipment choices for safer, more consistent cold exposure.

Cold plunge quotes help practitioners mentally prepare for ice baths, with purpose-built tubs like the OF-CP01 easing the daily routine.

The OF-CP01 cold plunge tank combines acrylic construction, PU insulation, a 1HP chiller, and filtration/ozone systems for consistent home or facility recovery use.

Evidence on whether cold plunging improves sleep remains limited and mixed, so timing, temperature, and individual tolerance matter more than any guaranteed outcome.

Cold plunging during menstruation is generally safe for healthy individuals if hygiene, flow protection, and personal comfort limits are respected.

Sacramento residents are turning to home cold plunge tubs like the OF-CP02, with chilling, insulation, and filtration features, for heat relief and recovery.

Ocean cold plunging offers potential health benefits but demands strict safety protocols, unlike controlled, consistent indoor cold plunge tub systems.

This guide covers planning a home cold plunge installation, detailing the OF-CP01’s chiller, insulation, filtration and electrical and structural requirements.

Cold plunge therapy’s physiological effects, safety protocols, and proper timing are examined alongside the OF-CP01 dedicated tub’s chiller, jets, and insulation features.

Newport Beach residents are turning to home cold plunge tubs like the OF-CP02 for coastal-ready contrast therapy and recovery routines.

Choosing a cold plunge kit involves balancing compressor power, insulation, filtration, and ozone sanitation, as seen in the integrated OF-CP01 system.

Lake cold plunging demands strict safety protocols for cold shock, hypothermia, and site hazards, with dedicated home tubs like OF-CP02 offering a controlled alternative.

Cold plunge ice requires substantial quantities and creates recurring costs, logistical challenges, and temperature inconsistencies that automated chiller systems with insulation can eliminate.

Cold plunge tubs may qualify for HSA funds when prescribed by a physician to treat specific medical conditions rather than for general wellness purposes.

Cold water immersion causes cardiovascular stress and requires medical clearance for those with hypertension.

Cold plunge heaters prevent freeze damage to outdoor tubs and enable dual-temperature contrast therapy in a single vessel.

Cold water immersion can trigger headaches through vascular, neurological, and muscular responses to sudden thermal shock.

Cold plunge gloves use neoprene insulation to retain hand warmth during ice baths.

Cold water immersion is riskier for children due to their physiology and lack of established safety protocols.

Installing a cold plunge in an apartment requires structural approval, proper drainage solutions, vibration isolation, and integrated systems to manage space and water safety challenges.

Cold plunge filters remove debris and protect chillers but must be paired with sanitizers to eliminate pathogens.

Cold plunge protocols may modestly influence metabolism through brown fat activation and thermogenesis, but sustained caloric deficit remains essential for fat loss.

Electric cold plunge systems automate temperature control, eliminating the need for manual ice purchases and setup time.

Cold plunge drainage systems use gravity drains or pumps to evacuate water safely while overflow ports prevent displacement flooding during immersion.

Cold water immersion triggers significant increases in plasma catecholamines like dopamine and norepinephrine through acute stress response mechanisms.

Cold plunge chillers use refrigeration to maintain precise water temperatures for recovery therapy.

Cold plunge dimensions involve balancing exterior footprint, interior basin size, structural load capacity, delivery clearances, and ventilation requirements for safe installation.

Cold showers may reduce sickness and improve alertness, though evidence is limited and plunge systems offer better temperature control.

Cold shock proteins are molecules studied for cellular protection during thermal stress.

The OF-CP01 cold plunge tub integrates a 1HP chiller, insulation, acrylic basin, and ozone filtration in one unit.

Hot tub prices are somewhat negotiable, depending on timing, dealer type, inventory, and how buyers frame the conversation.

Swim spas combine training and relaxation in one unit; analyzes cost, space, and dual-zone designs like the OF-1001U to assess real value.

Buying guide for compact 2-person hot tubs: seating, jet placement, insulation, sanitization, and lighting factors to consider.

Buying a backyard jacuzzi means weighing insulation, sizing, jets, filtration, and build quality over flashy extras.

Guide to choosing an 8-person hot tub: covers seating, jets, power, filtration, lighting, and material factors for group use.

Black Friday cold plunge deals require checking chiller power, insulation, filtration, and size, not just price—illustrated via the OF-CP01 as a case study.

Bromine suits hot tubs due to heat stability; effectiveness also depends on circulation, filtration, and insulation.

Compact 3-person spas can match larger tubs on jets, insulation, and filtration if engineered for three, not trimmed from six.

Dual zone swim spas separate swimming and therapy zones; key factors include jets, filtration, insulation, and controls, illustrated by the OF-1232BU.

Cold plunging may ease some autoimmune symptoms like joint stiffness, but it’s not a cure; consult a doctor and use controlled, hygienic equipment.

Explains base requirements for inflatable hot tubs and how a rigid cold plunge unit like the OF-CP01 avoids these foundation issues.

Above ground hot tub cost hinges on shell quality, insulation, jet/pump power, water care, and setup logistics, not just sticker price.

Guide to hot tub chemicals: sanitizers, pH, alkalinity, dosing routines, and how tub size, jets, and filtration affect maintenance.

Ice baths offer real recovery and mental benefits for some, but aren’t universally safe or superior to heat therapy—context matters most.

Guide to choosing a 6-person jacuzzi: seating, jets, heating, filtration, and layout tradeoffs for group use.

Guide to timing hot tub purchases for best discounts, using the OF-4001 5-person spa’s specs as a value comparison example.

Guide to pairing a 2 person ice bath with a hot tub like the OF-2001, covering sizing, jets, insulation, filtration, and maintenance.

Round spa for 5-6 seats: OF-V3004’s jet layout, insulation, filtration, and sizing considerations for buyers weighing capacity claims.

Guide to choosing a hot tub brand based on jet design, insulation, water care, and sizing, using the OF-4001 as an example.

Compares budget inflatable cold plunge tubs vs hard-shell chiller units like OF-CP01, weighing upfront cost against long-term value.

Hot tubs suit soaking, therapy, and social use, not swimming; pools remain better for exercise and laps.

Apple Watch不建议戴入热水浴缸,高温而非水深才是主要风险,会加速密封老化和电池损耗,建议入浴前取下手表。

Ostomates can safely use hot tubs with proper pouch prep, timing, and a jet layout like the OF-2001’s that avoids abdominal pressure.

Explores cold plunge benefits, risks, and who they suit, plus how equipment like the OF-CP01 tub improves temperature control and hygiene.

Guide to choosing an Alaskan cold plunge tub, covering chilling systems, insulation, hygiene, controls, and placement for home or facility use.

Explains how to choose swim spa covers based on insulation, sealing, and durability to cut heat loss and protect dual-zone spa equipment.

Compact hot tub buying guide covering jets, insulation, heating, and placement, using the OF-2001 as a size/spec example.

Guide to choosing a swim spa: dedicated swim pumps, filtration, jet placement, and matching features to fitness or recovery needs.

Cold plunge tub buying guide covering temperature control, insulation, hygiene, sizing, placement, and comparisons to ice-based setups.

Guide to choosing a 3-person outdoor spa: sizing, jets, insulation, heating, acrylic quality, and sanitization tips.

Hot tub water rarely spreads STDs; real risks come from poor sanitation causing bacterial infections like folliculitis.

Hot tubs ease fibromyalgia pain via heat and jet hydrotherapy, supporting sleep and circulation alongside medical treatment, not replacing it.

Pool salt corrodes hot tub equipment; use spa-rated sanitizers like chlorine, ozone, or dedicated low-salt systems instead.

Pregnant foot soaks in hot tubs are lower risk than full immersion if water stays under 100°F and sessions stay short.

Guide to modern cold plunge tubs, covering chiller tech, specs like OF-CP01, placement, and buying considerations.

Cold water accepts hot tub chemicals but dissolves them slower; proper dosing order and circulation prevent cloudiness before heating.

Cheap hot tubs often cut corners on pumps and insulation; smarter buyers weigh shell material, jets, and long-term energy costs.

Guide to choosing a cold plunge and hot tub combo, covering chiller systems, insulation, filtration, sizing, and placement.

Explains what drives backyard hot tub costs—size, jets, insulation, filtration—and how to match specs to actual household needs.

A 7×7 hot tub holds 350-450 gallons; seating design, pump sizing, and jet count affect fill time, heating, and water care.

DIY chest freezer cold plunges save money but lack insulation, filtration, and precise temperature control found in purpose-built tubs like the OF-CP01.

Hot tubs can be safe for kids with age-based limits on temperature, session length, and constant adult supervision.

Guide to choosing a 4-person jacuzzi, covering jets, pumps, insulation, filtration, lighting, and sizing considerations.

Babies should never use hot tubs due to hyperthermia, chemical, and drowning risks; safe use generally starts around age 5.

Pavers can support a hot tub if the compacted gravel base beneath is properly built for the spa’s filled operating weight, not just its dry weight.

Buying guide comparing China-made hot tub quality via jets, pump/heater wattage, insulation, sanitation, and sizing, using OF-6004 specs.

Compares 110V vs 220V hot tub wiring—cost, heat-up speed, jet power—using the OF-2001 spa to guide the right choice.

Examines evidence behind cold exposure and immunity claims, explaining physiological effects and key features for choosing a home cold plunge tub.

Buying guide for above ground jacuzzis: insulation, jet layout, filtration, shell material, and sizing considerations before purchase.

Cold compresses ease headaches via vasoconstriction; explains proper use, cold vs heat choice, and full-body cold immersion for recovery.

Huberman的冷水浸泡方案强调适度低温、短时、呼吸控制与持续性,专用冷浸桶通过恒温、计时和过滤系统降低坚持难度。

Hot tubs alone don’t damage the liver; risks stem mainly from alcohol, medication timing, session length, and water quality, not heat itself.

Explains what chlorine neutralizers do, when hot tub owners need them, dosing risks, and how ozone systems reduce overdosing.

Guide to choosing a backyard hot tub, covering sizing, jets, insulation, filtration, lighting, and audio, using the OF-V3004 as reference.

Hot tub water alone cannot cause pregnancy; heat affects sperm/fertility, and good sanitization and insulation matter more for safety.
Overshocking a hot tub can irritate skin, damage equipment, and waste money; proper dosing, testing, and weekly routines keep water balanced safely.

Swim spa value depends on pumps, zones, insulation, and filtration, not just price—OF-1001U shows how these factors compound long-term.

Brown stains on inflatable hot tubs come from metals, biofilm, or sanitizer residue; covers causes, removal steps, and prevention habits.

Guide to choosing a home cold plunge, covering chiller consistency, insulation, controls, ozone filtration, specs, and placement (OF-CP01).

Overview of what a 20-foot swim spa (e.g. OF-1638U) offers: counter-current swimming, hydrotherapy jets, filtration, insulation, and controls.

Explains what makes a home cold plunge system reliable: chiller, insulation, filtration, controls, placement, and maintenance.

Cold plunge therapy may temporarily boost dopamine/norepinephrine, helping some ADHD symptoms; consistency and equipment choice determine long-term success.

Compact two-person hot tubs like the OF-2001 can offer real hydrotherapy, strong insulation, and low running costs without the price of larger spas.

Hot tubs don’t burn fat directly but aid recovery, sleep, and stress, supporting long-term weight management alongside exercise.

Explains why black hot tubs suit modern yards, addressing heat myths, materials, and OF-6005 Pro specs to guide buying decisions.

Explains hot tub bubble mechanics—jets vs air, pump power, insulation, filtration—using the OF-2001 as a spec example for buyers.

Check deck weight capacity, drainage, and electrical needs before installing a hot tub; size the tub to fit your space and local codes.

Compares inflatable vs. rigid cold plunge tubs on insulation, filtration, durability, and control to guide long-term buying decisions.

Outdoor jacuzzi buying guide: shell material, insulation, jets, filtration, sizing, and features that ensure long-term durability.

Explains how cold plunges after massage affect circulation, ideal temperatures/durations, and what features to look for in a home tub like the OF-CP01.

60度冷水浴处于科学支持的恢复温区,靠隔热、制冷机组和覆盖盖板才能稳定维持而非仅靠冰块。

Cold plunge timing after eating affects digestion via blood flow competition; guide covers waiting windows and equipment like OF-CP01 for consistency.

Twice-daily cold plunging is safe for most healthy adults if sessions stay short, spaced apart, and purpose-driven, per recovery science.

Explains why hot tubs need a proper base instead of bare grass, comparing concrete, gravel, pavers, and decking options for safe installation.

Bromine vs chlorine hot tub sanitizers compared: stability, odor, cost, dosing, and how to pick the right fit.

Hot tub水关机后能否留存取决于时长:短暂停机通常安全,超过一周则建议排水或彻底做好化学维护。

热水浴缸生物膜成因解析:藏身管道难被发现,需靠日常清洁与臭氧/矿物过滤预防维护。

Backyard hot tub buying guide covering sizing, jets, insulation, filtration, lighting, and installation practicalities to match real usage needs.

Shopping for the best jacuzzi tub means sorting through jet counts, pump wattage, and insulation claims that all sound similar on paper. Most buyers get stuck comparing spec sheets without knowing which numbers actually change the daily experience. This guide breaks down the features that matter for outdoor hydrotherapy tubs, using a round 5-person model […]

Pacemakers keep hearts on rhythm, and hot water has a way of testing that rhythm. So it’s fair to ask: can you go in a hot tub with a pacemaker without putting your device or your heart at risk? The short answer is that many pacemaker patients do soak safely, but the decision depends on […]

Cold water immersion has moved from fringe wellness trend to something people actually schedule into their week. The interest in cold bath benefits isn’t just hype born from social media challenges; there’s a growing body of research behind why athletes, remote workers, and weekend warriors alike are stepping into chilly water on purpose. But separating […]

Plantar warts are stubborn, and soaking in warm water often sounds tempting after a long day. But if you’re wondering whether you can go in a hot tub with plantar warts, the honest answer is more complicated than a simple yes or no. Warts are caused by a virus, and warm, wet environments are exactly […]

Anyone shopping for advanced hot tubs eventually hits the same wall: every brand claims superior jets, better filtration, and smarter controls. The words start to blur together. What separates a genuinely capable spa from a dressed-up basic model isn’t a single spec sheet entry. It’s how the pump architecture, purification method, and seating geometry work […]

Shopping for the best 6 person hot tub usually starts with a simple question: will it actually fit your household and your yard? Most buyers underestimate how much jet count, pump power, and shell material affect daily comfort. This guide breaks down what separates a genuinely capable spa from one that just looks good in […]

Winter shouldn’t shut down a home hydrotherapy routine. Finding the best swim spa for cold climates means looking past marketing claims and focusing on insulation, pump efficiency, and how a unit actually behaves when the air outside drops below freezing. Anyone who has owned an outdoor spa in a northern region knows the anxiety of […]

Can you have sex in a hot tub? It’s one of the most searched questions among new spa owners, and the honest answer is more nuanced than a simple yes or no. Water, heat, and chemically treated environments interact with the human body in ways that matter for both safety and hygiene, and understanding those […]

Search for a blow up hot tub and you’ll find hundreds of listings promising spa-level relaxation for a few hundred dollars. Some deliver a decent soak. Many end up in a garage within a year, punctured or waterlogged around the pump housing. The gap between marketing photos and real-world durability is where most buyers get […]

Anyone asking can you put a hot tub indoors is usually staring at an awkward patch of yard, a rainy climate, or a bathroom that’s just sitting there unused. The short answer is yes, but the details matter more than the yes itself. Indoor placement changes how you think about ventilation, flooring, drainage, and even […]

Soaking in a hot tub after a long week feels like a reward, but a nagging question can take the shine off it fast. Can you get a UTI from a hot tub? The short answer is yes, it is possible, though the mechanism is often misunderstood. Hot tubs do not directly inject bacteria into […]

What Makes a Two-Person Hot Tub Different From Larger Spas Space dictates most backyard decisions before comfort ever enters the conversation. A best 2 person hot tub outdoor setup solves a problem that four and six-seat models create: wasted square footage nobody uses. Couples and small households rarely fill a large spa, yet they still […]

Anyone who has tried to fit a lap pool into a suburban backyard knows the math rarely works out. Space is limited, budgets are tighter, and most homeowners want more than just a place to float. This is where the benefits of a swim spa start to matter. A swim spa condenses the training value […]

Why People Convert Chest Freezers Into Cold Plunges Cold water immersion has moved from niche athletic circles into home wellness routines. Many people start their search by looking for the best chest freezer for cold plunge conversion, since a standard freezer seems like an affordable shortcut to icy water at home. The logic is simple: […]

A backyard spa pool changes the rhythm of a house. It gives tired shoulders somewhere to go after a long shift, and it gives weekends a reason to slow down. But before the water ever warms up, homeowners face a string of practical questions: how big should it be, what keeps it running efficiently through […]

Chlorine lock in a hot tub is one of the most frustrating water chemistry issues an owner can face. You keep adding sanitizer, the test strips still show weak readings, and the water starts to smell off despite your best efforts. This happens when chlorine gets bound up by excess chloramines or overwhelmed by high […]

Athletes have chased the same relief for decades: sit in the heat until the muscles let go, then drop into cold water until the mind goes quiet. That contrast is not a wellness trend. It is a physiological reset, and understanding the benefits of cold plunge and sauna use can change how you recover, sleep, […]

Why Plug-and-Play Models Appeal to So Many Buyers Anyone shopping for the best 110 volt hot tub is usually solving a specific problem: they want warm water therapy without ripping open a wall for a 220V circuit. A standard household outlet handles it, no electrician on speed dial required. That single fact changes the entire […]

Anyone who fills a tub with cold water and reuses it for days runs into the same problem eventually. The water turns cloudy, sometimes it smells faintly off, and skin that spent time in it starts to itch. Chlorine tablets for ice bath maintenance are one of the more common answers to this, borrowed straight […]

A 4 person hot tub sits at an odd crossroads in the spa market. It’s too small for the family-reunion crowd but often too roomy for a couple who just wants a quiet soak after work. That gap is exactly why so many buyers get the sizing decision wrong, then spend years wishing they’d gone […]

Runners chase a lot of things after a hard session: a foam roller, a protein shake, maybe a quiet stretch on the living room floor. Fewer of them think about water temperature, yet a cold plunge after running is one of the more direct ways to interrupt the swelling and soreness that build up in […]

Anyone shopping for a cold plunge 40 degrees Fahrenheit setup usually has one question buried under the marketing noise: is this actually cold enough to work, or just cold enough to be uncomfortable? The number itself gets thrown around loosely online, so it helps to separate what the temperature actually does physiologically from what it […]

Why Above Ground Hot Tubs Fit Most Backyards An above ground hot tub sits directly on a patio, deck, or reinforced pad without the excavation that in-ground models demand. That single detail changes everything about cost, timeline, and where the unit can go. Homeowners who want warm water therapy without a construction permit tend to […]

Searching for a cheap jacuzzi usually starts with sticker shock. Full-size spas can run into five figures, and that price tag pushes a lot of buyers toward compact two-person models instead. The good news is that a smaller footprint doesn’t have to mean fewer features. It just means being smarter about what you actually need […]

Shopping for the best 3 person hot tubs usually starts with a simple problem: you want the hydrotherapy experience of a full-size spa, but your patio, balcony, or budget won’t stretch that far. A 3-person hot tub solves the space equation without forcing you to give up jet power, heat retention, or water quality. The […]

Many people search "can baths cause yeast infections" after noticing irritation the day following a long soak. The short answer is that bathing itself rarely causes an infection, but certain habits around it can tip the balance toward one. Warm water, prolonged soaking, and residual soap can all disturb the natural microbial environment that keeps […]

Anyone shopping for a spa has probably wondered: can you buy a hot tub with HSA money and skip the extra cost? It’s a fair question, since these accounts exist to cover medical needs, and a hot tub sounds like it belongs in a wellness routine. The short answer is that it depends on documentation, […]

A swim spa is only as convenient as the effort it takes to keep it running. Automatic swim spa covers solve a problem that catches many new owners off guard: manually lifting a heavy, waterlogged cover twice a day gets old fast. For a unit stretching ten meters like a dual-zone swim spa, that chore […]

A barrel ice bath looks simple enough. Wood staves, a metal band, a hole for water. That simplicity is exactly why so many people buy one, then quietly wonder why the water warms up by afternoon or why algae shows up within a week. Cold exposure has moved from niche athletic practice into something closer […]

Can a hot tub fit through a door? It’s one of the first questions homeowners ask once they’ve picked a model, and it’s often answered too late. Getting the sequence backward, buying first and measuring second, leads to stuck deliveries, damaged doorframes, and spa units that end up parked in a driveway. The honest answer […]

Buying a cold plunge tub is only half the equation. The accessories around it determine whether your cold water immersion routine is safe, consistent, and something you’ll actually stick with. Anyone shopping for cold plunge accessories quickly discovers that the market is crowded with gadgets, but only a handful genuinely affect water temperature stability, hygiene, […]

Search "blow up cold plunge" and you will find two very different stories. One is about inflatable tubs that failed under pressure or seam stress. The other is a colloquial way people ask whether a cold plunge is worth setting up at all, as in "should I blow up (inflate) my cold plunge this weekend." […]

Shopping for a big outdoor jacuzzi usually starts with one question: how many people actually need to fit inside comfortably. A five-person spa sits in a practical middle ground, big enough for family nights or a small gathering, but not so oversized that it swallows a patio. Before comparing brands, it helps to understand what […]

If you’re asking can you heat a hot tub with the cover on, the short answer is yes, and it’s actually the correct way to do it. Heating an open spa wastes energy, extends warm-up time, and puts unnecessary strain on the heater. The cover isn’t just a safety accessory. It’s part of the thermal […]

Ask ten athletes when they cold plunge and you’ll get ten different answers. The best time of day to cold plunge actually depends on what you’re trying to fix. Morning sessions wake up a sluggish nervous system. Evening sessions, done carefully, can settle inflammation from a hard training day. There’s no universal clock time that […]

Anyone shopping for a compact spa eventually runs into the same question: how much does a 7×7 hot tub weigh with water, and can the deck or patio actually hold it. It’s not a trivial detail. A filled spa can weigh several thousand pounds, and getting that number wrong leads to cracked pavers, sagging joists, […]

Searching "cold plunge and cancer" usually means one of two things. Either someone read a headline linking cold exposure to tumor suppression, or someone undergoing treatment wants to know if cold water immersion is safe for their body. Both questions deserve honest answers, not wellness-industry hype. This article looks at what’s actually known about cold […]

Cloudy hot tub water is one of the most common frustrations spa owners run into, and it rarely means something is broken. Most of the time, it’s a signal that water chemistry, filtration, or circulation needs attention. Understanding what causes the haze helps you fix it faster and keep your soak time enjoyable. What Cloudy […]

Shopping for a hot tub usually starts with a simple question: which model actually holds up once the novelty wears off? Best rated hot tubs earn that status through jet performance, water care systems, and build quality that survives daily use, not marketing copy. This guide breaks down the features that separate a genuinely good […]

Cold water immersion has moved from niche athletic recovery circles into mainstream wellness routines. Yet the question "are ice baths dangerous" comes up constantly among people considering their first plunge. The honest answer is nuanced. Ice baths carry real physiological risks if approached carelessly, but with proper preparation and equipment, most healthy adults can practice […]

If you’ve ever stepped out of a steamy sauna and wondered whether a cold shower after would help or hurt your hair, you’re asking the right question. Are cold showers better for your hair, especially post-sauna, is one of those debates that sounds simple but touches on real scalp physiology. Heat opens things up. Cold, […]

Periods have a way of showing up right when you had plans. Maybe you booked a weekend at a villa with a private spa, or maybe your own backyard hot tub is calling after a long week. So the question lands honestly: can you go in a hot tub on your period, or should you […]

If you own a spa, you have probably asked yourself: can I turn the heater off on my hot tub without causing damage? The short answer is yes, but the longer answer depends on your climate, how often you use the tub, and what kind of insulation your unit has. Understanding when to shut the […]

Anyone who has stared at a cloudy hot tub and then glanced at the bleach under the sink has wondered the same thing. Can you use bleach in a hot tub to fix cloudy or smelly water fast? The short answer is no, and the reasons involve chemistry, plumbing materials, and your own skin. This […]

Buying a 220v hot tub means dealing with real electrical planning, not just picking a color and a jet count. Most two-person spas, including compact residential models, are built around this voltage because it delivers enough steady power to run a pump and heater together without tripping breakers every time someone turns on the bubbles. […]

Searching for the best spas for backyard installation usually starts with a simple frustration: most spa listings read like spec sheets, not solutions. You want warmth on a cold evening, room for guests, and water that stays clean without constant babysitting. That’s a fair set of demands, and it narrows the field faster than most […]

Why Family Size Changes Everything About Hot Tub Shopping A 7 seater hot tub sits at an odd crossroads in the spa market. It’s large enough to host a small gathering, yet compact enough to still fit most residential patios without major structural work. That middle ground is exactly why so many buyers land here […]

If you have ever stood in the pool chemical aisle holding a jug of calcium hypochlorite, wondering whether it belongs in your spa, you are not alone. The question "can I use pool shock in my hot tub" comes up constantly among new owners who assume pool and spa water care work the same way. […]

Foamy water in a spa is one of those problems that seems minor until you’re standing over a tub full of froth instead of clear water. Many owners immediately blame their soap or lotion residue, but the real culprit is often chemistry. Can low pH cause foam in hot tub water? Yes, and understanding why […]

Warmer months bring a common question for spa owners: can i turn off my hot tub in the summer without causing damage or headaches later? The short answer is yes, but the "how" matters more than the "if." Shutting down improperly can lead to stagnant water, component strain, or a spa that struggles to restart […]

Finding the best inflatable hot tub often starts with a simple problem: not enough space, but plenty of desire for warm water therapy after a long day. Many buyers assume inflatable models mean flimsy walls and weak jets, but that gap has narrowed. This guide breaks down what actually separates a durable, comfortable unit from […]

A big hot tub changes how a backyard gets used. Instead of a corner that sits empty most evenings, you get a spot where five people can soak, talk, and unwind after a long week. For families who host often or simply want room to stretch out, the seating capacity of a spa matters as […]

A 4 person hot tub outdoor setup sits at an odd intersection of practicality and indulgence. It has to fit a patio without swallowing it whole, yet still deliver the kind of soak that makes the cold months bearable. Shoppers usually land here after realizing that a two-person model feels cramped once guests show up, […]

Cold plunging has moved from niche athletic recovery tool to a daily ritual for people chasing better sleep, sharper focus, and less inflammation. But the best time to cold plunge isn’t a fixed rule stamped on a wellness calendar. It depends on your goal, your nervous system, and how your body responds to sudden cold […]

Shopping for the best budget hot tub means balancing upfront cost against jets, insulation, and long-term running expenses. Most buyers overspend on features they never use, or underspend and end up with a tub that leaks heat and drains their power bill. The real question isn’t "cheap versus expensive." It’s whether a compact, well-insulated unit […]

Bath bombs look harmless enough. A little fizz, a puff of color, maybe a scent that reminds you of a spa day. So it makes sense that plenty of hot tub owners wonder, can you put bath bombs in a hot tub the same way you’d drop one into a bathtub. The short answer is […]

Most spa owners eventually ask the same question after installing a new unit: can you use hot tub during filter cycle, or should you wait until the water finishes its scheduled treatment? The short answer is yes, in nearly every case. Filtration and heating cycles are designed to run continuously or on a timer, and […]

An 8 person jacuzzi sits at an odd crossroads. Most backyard hot tubs top out around five or six seats, so once a household wants room for larger gatherings, the shopping list gets short fast. This guide walks through what actually separates a genuine group-capacity spa from a tub that just looks big in a […]

The Short Answer, and Why It Matters More Than You Think Can you put Epsom salt in a hot tub? The technical answer is yes, physically nothing stops you from pouring it in. But whether you should is a different question entirely, and it depends on the type of spa you own. For acrylic hot […]

A 19 foot swim spa sits in an unusual middle ground. It is longer than almost any traditional hot tub on the market, yet it takes up far less space and costs considerably less to install than a lap pool. For homeowners weighing swim training against square footage, and for boutique wellness operators trying to […]

Why Size Changes Everything in a Spa Purchase A big jacuzzi is not just a larger version of a small spa. It changes how water moves, how heat is retained, and how many jets actually reach a body sitting inside. Homeowners often assume bigger simply means more room, but the engineering underneath shifts too. Pumps […]

If you’re wondering whether you can wear a tampon in a hot tub, the short answer is yes, but there are a few things worth understanding first. Heat, water pressure, and soak time all interact with menstrual products in ways that aren’t always obvious. This matters whether you’re easing into your own backyard spa or […]

Cold water has been used for recovery long before it had a marketing name. Nordic villages built ice holes into frozen lakes, and Roman bathhouses reserved a cold room, the frigidarium, for the final stage of the ritual. The modern arctic cold plunge is that same idea, engineered into a compact tub that fits on […]

A 4 person round hot tub sits in a strange middle ground. It’s too small for a party of eight, but it’s also not a cramped two-seater squeezed onto a balcony. For couples, small families, or anyone with a compact patio, that middle ground is exactly the point. The round shape matters here too, since […]

Buying a hot tub is the easy part. Getting permission to keep it in your backyard is where things get complicated for homeowners under a homeowners association. Yes, an HOA can deny a hot tub, and understanding why turns a frustrating rejection into a manageable approval process. Most HOAs don’t ban hot tubs outright. Instead, […]

Cold plunging has become a fixture of recovery routines, but the question "can you cold plunge with Raynaud’s syndrome" stops a lot of people before they ever step in. Raynaud’s affects blood flow to the fingers and toes, and cold exposure is the exact trigger doctors warn about. That does not automatically mean cold plunging […]

Why Seating Capacity Changes Everything A hot tub built for four people solves a specific problem: enough room for a couple or small family without the footprint and running costs of a larger spa. Shoppers searching for the best 4 person hot tub usually want something that fits a patio corner, doesn’t overwhelm a deck’s […]

Gravel looks like an easy answer when you’re staring at a bare patch of yard and a delivery date. So the question comes up constantly: can you put a hot tub on gravel, or does that shortcut cost you a cracked shell six months later? The honest answer is that gravel can work, but only […]

If you have ever caught a whiff of chlorine at the pool and wondered whether that same logic applies to your backyard spa, you are asking the right question. Are hot tub chemicals bad for you, or is that reaction more about misuse than the chemistry itself? The honest answer sits somewhere in between, and […]

An acrylic hot tub is only as good as the details buyers skip past. Shell thickness, jet layout, and insulation quality decide whether a spa holds up through a decade of use or turns into a costly repair project. This guide breaks down what actually matters when shopping for a round acrylic hot tub, using […]

Why 50 Degrees Comes Up So Often in Cold Plunge Talk Anyone shopping for a cold plunge eventually runs into the number 50. It shows up in forums, product listings, and recovery blogs like a password everyone assumes you already know. In Fahrenheit, 50 degrees sits at the cooler end of what most physiologists consider […]

Anyone sharing a backyard spa with a curious dog has probably wondered: can dogs go in hot tubs safely, or is that water strictly a human-only zone? The short answer is that hot tubs are not designed for dogs, and letting one soak alongside you creates real risks for both the animal and the equipment. […]

Shopping for the best affordable hot tub often starts with a simple frustration: most listings either skimp on real specs or bury you in marketing language. Buyers want warmth, working jets, and a shell that survives seasons outside. This guide breaks down what actually separates a budget hot tub from a poor one, using real […]

A backyard tub pool changes the rhythm of an evening. Instead of driving to a spa or waiting for a weekend getaway, you step outside and sink into warm water within minutes. The appeal is obvious, but choosing the right unit is less straightforward. Size, insulation, jet configuration, and water care systems all affect whether […]

A 45 degree cold plunge usually refers to the camera angle used in product photography, not a tub tilted at that pitch. But the phrase has quietly become shorthand for something else too: the way people search for a clear, honest look at what a single-person cold plunge actually looks like before they buy one. […]

Shopping for the best garden hot tubs usually starts with a simple question: will this thing actually hold up outside, and will it feel good enough to use twice a week instead of twice a year? Those two concerns drive almost every decision that follows, from shell material to jet layout. This guide walks through […]

A gym owner in Colorado once told me he replaced his cold plunge twice in eighteen months. Not because members disliked it. Because the chiller couldn’t keep pace with back-to-back athlete sessions, and the acrylic shell cracked under freeze-thaw stress from an unheated storage room. Choosing the best commercial cold plunge isn’t about finding the […]

Stepping toward icy water triggers a very specific kind of dread. Cold plunge anxiety is common, and understanding why your body reacts this way is the first step toward a calmer, more consistent practice. Why Cold Water Triggers a Fear Response The moment skin meets cold water, the body activates its sympathetic nervous system. Heart […]

Pregnancy changes how your body handles heat, pressure, and buoyancy, so the question of whether pregnant women can go in hot tubs comes up for good reason. Warm water eases swollen ankles and tight lower backs, but a standard hot tub often runs hotter than what’s considered safe during pregnancy. Understanding the actual risk, and […]

The Difference Between Bubbles and Real Hydrotherapy Anyone shopping for a spa eventually asks the same question: why do bubbles in hot tub water feel so different from a regular bath. The answer sits in engineering, not magic. Air alone creates a light fizzy texture, similar to a soft drink. Water jets, on the other […]

A 2 person hot tub solves a problem that larger spas create: not everyone has the yard, the budget, or the desire to heat a six-seat basin just to soak after work. Compact doesn’t have to mean cramped, though, and the right unit can deliver real hydrotherapy in a footprint that fits a patio corner […]

Anyone shopping for the biggest hot tub usually starts with one question: how many people actually need to fit inside without elbows knocking together. A crowded tub defeats the purpose of relaxing, and an oversized one can turn into wasted water and energy. Finding the right balance between seating capacity, jet performance, and running costs […]

Shopping for the best hot tubs means sorting through jet counts, insulation claims, and seating layouts that all sound similar on paper. The real question is simpler: will this tub actually fit how you live, recover, and unwind. A six-person spa with dozens of jets solves a different problem than a compact two-seater tucked into […]

Anyone chasing the benefits of cold water immersion eventually hits the same wall: buying ice by the bag gets old fast. Searching for a cold plunge alternative usually starts here, at the intersection of convenience and cost, and it points toward equipment that keeps water cold without the daily hassle. The good news is that […]

Standing over a cloudy hot tub with a bottle of household bleach in hand is a familiar moment for a lot of owners. The water looks off, there’s a faint smell you don’t trust, and bleach is sitting right there under the sink. So can you use bleach to clean a hot tub safely? The […]

A 2 person corner hot tub solves a specific problem: you want the ritual of hydrotherapy without giving up half your patio to do it. Corner-friendly, compact outdoor spa designs have become the default choice for couples working with tight backyards, rooftop decks, or rental properties where every square foot counts. That demand didn’t appear […]

Shopping for the best outdoor hot tubs means balancing comfort, durability, and running costs against how you actually plan to use the tub. A weekend soak with friends demands different features than nightly therapy for sore shoulders after training. This guide breaks down the technical details that separate a decent spa from one that holds […]

A cedar cold plunge has a certain appeal that’s hard to argue with. The wood grain, the earthy smell, the way it looks like it belongs next to a sauna rather than a swimming pool. For a lot of people searching for a cold plunge, cedar is the first material that comes to mind because […]

If you’re wondering "can i put an inflatable hot tub on my deck," you’re likely weighing cost against convenience. Inflatable models are cheap and easy to find, but decks introduce weight, moisture, and structural questions that many buyers overlook until it’s too late. This guide walks through what actually matters before you fill one with […]

小户外空间选购单人按摩浴缸指南:解析尺寸、喷嘴布局、保温与水质维护要点,帮助买家在预算与体验间做出合理选择。

本文解析7人浴缸尺寸背后的容易被误导之处,涵盖占地面积、注水重量、安装间隙、喷头数量与保温设计,帮助买家理性判断实际舒适度。

选购六人户外浴缸需综合考量座位设计、喷头布局、保温加热及水质维护,而非只看容量数字,才能确保长期实用与耐用。

50度冷水浴是恢复训练的理想温度区间,文章分析其生理效果,并介绍OF-CP01一体式制冷浴缸如何通过保温、过滤和恒温系统解决传统冰浴的不稳定问题。

6人浴缸选购需综合水量、泵功率、喷嘴分布、过滤系统与隔热配置,以OF-6002 Pro为例说明如何按实际使用场景匹配规格。

OF-2001两人温泉浴缸解析110V与220V电压差异,凭紧凑设计、22个按摩喷头、隔热层与臭氧过滤,适合公寓、露台等免电工安装场景。

六人浴缸的价格差异主要取决于泵和加热器功率、喷嘴配置、外壳保温材料及过滤系统,这些结构性因素共同决定长期使用成本与体验,而非单看标价高低。

55度冷水浸泡兼顾疗效与安全,关键在于设备能否稳定控温;文章解析其生理作用、选购要点及OF-CP01等冷水浴缸的设计考量。

4座按摩浴缸价格差异主要由喷嘴配置、泵功率、隔热材料和过滤系统决定,而非座位数,选购时应综合比较这些配置而非只看价格。

四人浴缸价格差异大,主要取决于外壳材质、喷头数量、泵功率、保温性能及电控配置,选购应结合实际使用需求综合评估性价比。

5分钟冷水浸泡的生理机制、温度控制的重要性、常见误区及冷水浴与专业冷浸缸的差异,助力养成持久有效的冷疗习惯。

5人浴缸兼顾家庭与社交需求,需综合考量座位设计、喷嘴布局、能耗保温及水质维护,以OF-4001为例说明选购要点。

30英尺泳池SPA兼具训练与康复功能,通过对流系统、多级过滤和智能控制满足全年户外使用需求,选购前需综合考量场地、电力及使用目标。

40度冷水浸泡在耐受与效果间取得平衡,配备专用冷水机、数显控制、臭氧过滤和保温设计的单人浴缸,可解决冰浴温度不稳、维护繁琐等问题,让恒温冷疗成为可持续的日常习惯。

3人小型按摩浴缸适合空间有限的庭院或阳台,兼具喷嘴布局、保温、水质净化与氛围灯效等设计,以OF-3001为例说明如何按需选购。

单人浴缸看似省空间,但需求常随时间变化。文章对比单人与OF-V3004五人圆形按摩浴缸,从保温、水疗喷头、过滤系统等方面说明为何稍大尺寸更耐用实用。

5人按摩浴缸兼顾家庭聚会与阳台空间,需综合考量喷嘴布局、功率、保温、水质净化及照明等因素后再决定购买。

小尺寸2人户外泡浴缸兼顾空间与功能,配备22个按摩喷头、保温层、臭氧净化及氛围灯光,适合阳台、屋顶及小院使用。

小型双人户外按摩浴缸兼顾水疗效果与空间限制,本文从喷头布局、外壳材质、保温层到灯光音响,解析选购要点及适用场景。

OF-2001双人按摩浴缸专为小空间设计,兼具定向水疗、多层保温、臭氧净水等功能,适合日常个人使用而非聚会场景。

“15人热水浴缸”搜索背后其实是场地和聚会需求,但过大浴缸会稀释水疗效果并增加能耗,精心设计的4人浴缸(如OF-6006 Pro)往往更实用。

14英尺泳池SPA兼具游泳训练与水疗功能,选购需关注泵功率、过滤系统、按摩喷头布局及用电需求,而非仅比较品牌与外观。

120V热水浴缸插标准插座即可使用,免电工免许可但加热较慢;240V硬接线系统功率更高,加热快、支持更多喷头,适合日常重度使用家庭。

120伏热水浴缸可直接接入标准家用插座,无需240伏专用线路或电工改造,特别适合租户、公寓业主及小型空间。以OF-2001为例,配备22个喷嘴、臭氧净化系统和多层保温设计,在紧凑双人布局中实现集中水疗效果。虽然加热速度较慢,但通过优化绝缘和喷嘴密度,在降低安装成本的同时保持实用性能,更契合实际使用场景而非单纯追求规格参数。

110V热水浴缸无需专线电路,插电即用,兼顾便利与性能,适合小型住宅、露台及出租房,重点在保温、水泵与喷头设计。

100加仑饲料槽可作冷水浴但缺乏保温、喷射与过滤系统,若追求恒温水疗、按摩或社交泡浴,专业热水浴缸如OF-V3004更具优势。

搜索”10人水疗浴缸”的买家通常追求容纳人数,但标称容量与实际舒适度存在巨大差距。大型浴缸水量、加热、维护成本高,而多数家庭实际使用仅2-4人。像OF-6006 Pro这样的4人浴缸配备59个喷嘴、双泵系统和优质绝缘,在喷嘴密度、按摩质量和运行成本上往往优于稀疏布局的10人浴缸,更符合真实使用场景。

选购单人户外按摩浴缸时,外壳材质、隔热层、射流布局与过滤系统才是决定舒适度的关键,而非座位数量或喷嘴总数。

本文讲解10分钟冷水浸浴的生理反应、时长与温度关系,并介绍如何通过专业冷水浴缸设备实现更稳定、安全、可持续的冷疗恢复routine。

本文详解4人户外按摩浴缸的选购要点,涵盖尺寸、喷嘴布局、保温性能、水质净化及照明配置,帮助买家理性对比规格并合理安置使用。

While the evolution of aquatic therapy has driven a critical shift from basic, turbulent jets to Precision High-Flow River Currents, delivering a smooth, flat, and continuous swimming experience is only half of the equation. To safely contain and sustain the massive volume of water required for advanced swim lanes, the physical vessel must be engineered […]

When investing in a premium swim spa, modern homeowners, commercial developers, and distributors look for two essential factors: uncompromising aquatic performance and the flexibility to customize the spa to exact specifications. Legacy swim spas often fail to deliver on both, offering fixed, rigid layouts and choppy water currents that create unpleasant splashing. The Ocean Future […]

For decades, outdoor living design focused almost entirely on traditional, static features—a quiet patio, decorative landscaping, or a simple swimming pool. But in today’s fast-paced, health-conscious landscape, the modern luxury real estate market has reached a clear inflection point. Homeowners no longer want a backyard that just looks good—they want an active environment that restores […]

For decades, the standard blueprint for high-end residential luxury was defined by a massive, in-ground concrete swimming pool. It was a visual statement piece, but one that came with severe operational liabilities: massive spatial consumption, exorbitant year-round heating costs, complex civil engineering, and months of winter downtime. As we move through 2026, the global luxury […]

The global elite’s resistance to harsh chemical pool treatments like chlorine has officially reached its peak. Modern high-performers refuse to compromise their biological integrity, gut microbiomes, or skin barriers just to keep their pool water clear. The industry solution dominating discussions this week is the integration of Nanobubble Technology paired with Advanced Hydro-Filtration. [ Traditional […]

Historically, the premium wellness market operated on a simple premise: if you wanted to detoxify and optimize your health, you bought a traditional wooden sauna box for your home. You turned up the temperature, sat inside, and assumed the sweating process was doing its job. But as we advance through 2026, the elite wellness consumer […]

As we move further into 2026, the definition of luxury has undergone a radical transformation. High-net-worth individuals and forward-thinking developers are no longer just asking, “Does this property look impressive?” They are asking, “How does this property optimize my health?” Welcome to the era of Home Bio-Hacking. Beyond the Gym: The Rise of the “Longevity […]

Meta Description: Dislike the strong chlorine smell and red eyes from traditional pools? Discover how Ocean Future Spas utilizes advanced saltwater electrolysis and multi-stage micron filtration to deliver “skin-friendly,” crystal-clear water for your family. Summer is in full swing, and across North America and Europe, families are looking for ways to beat the heat. However, […]

If you are a luxury property developer, landscape architect, or custom homebuilder operating in today’s market, you’ve likely noticed a radical shift in backyard design aesthetics. The traditional, bright “motel blue” chlorinated swimming pool is rapidly disappearing from high-end architectural blueprints. In its place, a new standard has emerged: deep charcoals, slate grays, and midnight […]

As summer heatwaves intensify, high-end property owners are investing in a complete summer heat acclimation sauna swim spa setup to build physical tolerance against extreme outdoor temperatures. While the instinctual response to rising humidity is to hide indoors under the air conditioning, the global longevity community is utilizing deliberate thermal conditioning to drop their baseline […]

If you have tried getting a quote for a traditional concrete pool installation recently, you already know the backyard renovation market has hit a point of breaking. Between soaring contractor labor rates, municipal permit delays that drag on for eight months, and local water restriction orders in several regions, digging a massive hole in the […]

Let’s be completely honest. When it’s the middle of July, and the outdoor humidity makes the air feel like warm soup, the last thing on your mind is crawling into a hot box to sweat. For decades, there’s been a common myth that home saunas are strictly a winter luxury—something you only turn on when […]

Let’s be real for a second. We’ve all envisioned the perfect summer: a sparkling blue pool in the backyard, kids splashing around, and you lounging pool-side with a cold drink. It’s the ultimate dream, right? But as anyone who has actually gone through the process of building an old-school concrete pool will tell you… the […]

ummer temperatures are climbing across Europe and North America. Landscape architects and premium homeowners now face a shared challenge. This challenge is Eco-Anxiety. Prolonged heatwaves are triggering strict water restrictions across many regions. Therefore, many people need a sustainable luxury pool alternative. They want to keep their summer lifestyle intact. However, they must avoid draining […]
Imagine lacing up your running shoes at 7 a.m. and already feeling sweat bead down your back. By 8 a.m., you’re drenched, exhausted, and ready to call it quits. Or worse—you drag yourself to the gym, only to fight for a machine in a stuffy, overcrowded room where the air smells like stale sweat. This […]

Integrating a daily sweat session is a foundational longevity practice for modern biohackers and athletes looking to accelerate muscle recovery. However, as home units become more popular, a critical safety question arises: are infrared saunas safe for daily use? The answer is yes—but only if the cabin environment is chemically pure. When operating a compact […]

In today’s fast-paced world, carving out time for self-care shouldn’t require a trip to a crowded spa or a dedicated room in your home. For anyone who’s dreamed of having a sauna but thought they didn’t have the space—or hated sharing a steamy room with strangers—small single-person saunas are the game-changing solution. They combine all […]

An infrared sauna room is one of the most popular options because it delivers gentle, targeted heat without the extreme temperatures of traditional saunas. Instead of warming the air, infrared panels warm your body directly, which many people find more comfortable and easier to tolerate. Regular sessions may support relaxation, stress reduction, and muscle recovery. […]

In the pursuit of peak human performance, the sauna has evolved from a traditional luxury into a critical tool for metabolic health. However, the efficacy of heat therapy is entirely dependent on the integrity of the environment. At Ocean Future, the OFS-04 Series represents our most advanced engineering response to the demands of modern longevity […]

Looking for a private home sauna but worried you don’t have enough space? The OFS06A-1 single-person sauna is exactly what you need. No need for a big backyard, no need to remodel your house. This compact sauna fits perfectly in bathroom corners, spare rooms, home gyms, apartment nooks, even your bedroom side space. We built […]

In the chaos of modern life, genuine relaxation and consistent wellness care often feel out of reach. Public spas come with crowded spaces, inflexible hours, and awkward small talk, while traditional saunas often deliver stifling, overly hot air that leaves you feeling drained instead of refreshed. What if you could bring professional-grade thermal therapy home, […]
Before buying an infrared sauna, the top question for 90% of consumers is: “Is it really safe?” Unlike traditional steam saunas, infrared saunas use far-infrared radiation to heat the body directly, which leads to many safety concerns. This guide, based on research from the FDA, Mayo Clinic, and Harvard Health, answers all your safety questions […]

In the world of high-end wellness, we often hear the term “Duru”—a Turkish word signifying purity, clarity, and a state of being untouched. Achieving this “Duru” state in our chaotic, modern lives requires more than just a quick shower. It requires a systemic intervention. At the intersection of ancient recovery traditions and modern engineering lies […]

In the fast-paced world of modern wellness, few practices have stood the test of time as effectively as heat therapy. While once considered a luxury reserved for high-end spas, the modern sauna room has evolved into a sophisticated health tool. Today, it sits at the intersection of ancient tradition and cutting-edge physiology, offering a dual-action […]

When most people think of a hot tub, they picture a weekend of relaxation or a social centerpiece for a party. But for those of us in the manufacturing industry, we see a hot tub as a sophisticated piece of hydrotherapy equipment. So, are hot tubs actually good for you? The short answer is a […]

At-home heat therapy is booming. But with so many products flooding the market, it’s easy to be misled by overstated marketing claims. Let’s cut through the hype. Here is the factual, engineering-level breakdown between portable sauna blankets and true traditional home saunas—so you can make an informed investment in your health. Quick Product Overview Infrared […]

The short answer is yes, infrared saunas are safe, but the real risks are invisible and often ignored by retail brands. As a manufacturer, we look past the “light” and focus on the two critical factors that determine if your sauna is a health sanctuary or a chemical hazard: Air Quality and EMF Shielding. The […]

Walk into any luxury gym or wellness center, and you’ll hear the claim: “Burn 500 calories just by sitting in the sauna.” It sounds like the ultimate “biohack” for weight loss. But as a manufacturer focused on engineering and biological safety, we believe in giving you the unfiltered truth. Can a sauna help you lose […]

For many wellness enthusiasts, the dream of a home sauna is often crushed by two words: “The Lease.” Standard high-heat saunas usually require permanent installations, 240V electrical upgrades, and a heavy footprint that simply doesn’t work for a rental property. On the other end of the spectrum, the market is flooded with low-cost “sauna tents” […]

In 2026, the global conversation around health has shifted from “treating illness” to “optimizing longevity.” We are no longer just looking to live longer; we are looking to live better. This is the essence of Preventive Wellness, and at the heart of this movement is a centuries-old practice backed by modern science: the sauna. 1. […]
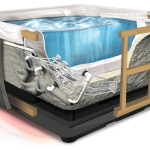
Discover the OF-6004, a 6-person luxury spa. This detailed review goes beyond the marketing fluff to expose the engineering secrets—including Lucite®/Aristech® multi-layer acrylic, targeted 316 stainless steel jets, high-efficiency insulation, and certified Balboa® controls. Plus, see a real installation spotlight from the online spa community! 1. Beyond the Surface: What Real Spa Owners Actually Care […]
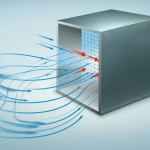
Looking for a safe far-infrared sauna? Most “Low EMF” marketing ignores ELF (Extremely Low Frequency) and toxic glue off-gassing. To ensure safety and performance, prioritize combined EMF/ELF shielding, solid Tongue and Groove construction (no glues), and certified control systems (ETL/CE). 1. The Invisible Risk: EMF vs. ELF Shielding Most consumers search for “Low EMF saunas,” […]

Part I: The Hidden Traps – Why Cheap Hot Tubs Cost More Over Time When most first-time buyers evaluate a professional-grade hot tub, they are often captivated by aesthetic features like cascading waterfalls or Bluetooth speakers. However, from the perspective of a sanitary ware R&D professional, these are merely surface-level distractions. The true value of […]

Part 1: Why Does Excessive Foam Appear After a Fresh Water Change? 1. The Hidden Culprit: Biofilm Even if you regularly use Bromine or other sanitizers, they only kill free-floating bacteria in the water. They struggle to penetrate Biofilm—a stubborn, protective layer that clings to the inside of your plumbing, shielding colonies of bacteria and […]

“We recently saw a common question on Reddit from a user in Florida wondering if they should cycle their cold plunge chiller between 50°F and 60°F to save energy. At Ocean Future, our engineering team has a different take: Stability is king.” Part 1: The Common Cold Plunge Chiller Question, Answered The short answer? Don’t […]

If you’re planning a DIY backyard wood stove sauna, you’ve probably run into the two most popular build options: thick T&G (Tongue & Groove) no-insulation walls, and framed insulated sauna walls. Which one fits your needs? We’re breaking down the real-world pros, cons, and tradeoffs to help you pick. Thick T&G (No Insulation) Sauna: The […]
We often say that the best relaxation sessions aren’t just about the water—they’re about the atmosphere you create. Imagine the perfect evening: a curated playlist on the speakers, a chilled drink in hand, and the steam rising into the night air. It’s an experience that should be savored, not rushed. However, the ultimate “mood killer” […]

The Frustration: You’ve dumped gallons of liquid chlorine and bags of shock into your pool, yet the water remains a stubborn, cloudy green. It feels like a losing battle against nature. But the problem isn’t the amount of chemicals—it’s the Chemistry. The Culprit: Cyanuric Acid (CYA) Overload Most pool owners use stabilized chlorine tablets (trichlor). […]

OFS01-3 infrared sauna delivers deep relaxation, improved circulation, and modern home wellness.

OFS01-3 far-infrared sauna delivers premium home wellness, relaxation, and detox benefits.

OFS01-3 infrared sauna room offers ultimate relaxation, detox, and wellness at home.

OFS01-1 infrared sauna delivers advanced health, relaxation, and detox benefits for home use.

Transform your wellness routine with the OFS01-1 infrared sauna for relaxation and detox.

Experience the OFS01-1 infrared sauna for relaxation, detox, and enhanced home wellness.

Discover the OF-120AT swim spa for fitness, hydrotherapy, and year-round home wellness.

OF-120AT swim spa delivers training, hydro-massage, smart entertainment, and energy-efficient relaxation.

OF-120AT swim spa delivers exercise, hydro-massage, and energy-efficient relaxation for the whole family.

OF-120T swim spa delivers compact fitness, hydrotherapy, and family relaxation at home.

OF-120T swim spa delivers fitness, hydrotherapy, and luxury in one compact design.

OF-120T swim spa combines elite fitness training with luxury hydrotherapy relaxation.

Shop the OF-3001 Pro hot tub for luxury, efficiency, and ultimate outdoor relaxation.

Discover the OF-2001 Pro hot tub, blending smart relaxation with premium spa comfort.

Explore why the OF-3001 Pro hot tub leads in performance, design, and relaxation.

Discover the OF-2001 Pro hot tub with premium comfort, relaxation, and hydrotherapy.

Experience the OF-R001 patio hot tub with hydrotherapy, energy efficiency, and entertainment.

Discover the OF-R001 hot tub with 38 jets, insulation, and Bluetooth entertainment.

Discover the OF-R002 hot tub with hydrotherapy, energy efficiency, and family-friendly design.

Experience the OF-R002 hot tub with reliable heating, strong jets, and family-friendly design.

Soaking in a hot tub, enveloped in steam amid the gentle bubbling of water, connotes leisure and escape.

Hot tubs combine human-centric design and environmental responsibility.

These hot tubs, silently lined up will in the future becomeA vessel of happiness for many families:Some people wash away their fatigue here.Children play and grow up here.Couples share their mornings and evenings here…And right now, we’re putting the finishing touches on these stories.

The hot tub relaxes the body with heat, thereby drawing away the accumulated fatigue and stress from the day. It also creates ideal conditions to slip into a deeper sleep by increasing blood flow and regulating temperature. Scientific studies have proven that hot baths can bring a very good improvement in sleep quality, thus making […]

When deciding between a swim spa and a hot tub, it’s critical to take your wellness goals, lifestyle, and personal preferences into account. Although both choices promote relaxation and reduce stress, they have different functions and unique characteristics. Knowing the distinctions between a swim spa and a hot tub will enable you to choose the […]

An excellent addition to your home is an outdoor spa tub, which offers you a tranquil haven where you can unwind, revitalize, and spend time with your family and friends. However, routine care is necessary to keep the bathtub clean, functioning, and attractive. Maintaining the best possible condition for your outdoor spa tub not only […]

Swim spas are a modern addition to many homes, offering a mix of fitness, relaxation, and fun in one. These versatile water systems have gained widespread popularity over the years since they can do what swimming pools and hot tubs can singly offer in just one compact unit. Be an athlete in need of increasing […]

Hot tubs have evolved significantly over the years. From the simplest concept of relaxation equipment to design innovations, technology has transformed it into a luxury product with therapeutic benefits. A modern hot tub is designed for comfort and relaxation, featuring advanced technology for users. This passage explores the evolution of hot tub design and the […]

Investing in an outdoor spa is a great way to enhance your lifestyle, offering a tranquil retreat where you can relax, unwind, and rejuvenate. Whether you want to create a luxurious backyard oasis or simply enjoy a soothing soak after a long day, the right outdoor spa can make quite a difference. With so many […]

In today’s fast-paced world, where stress is an inevitable part of everyday life, finding ways to relax and rejuvenate is essential to maintaining a healthy body and mind. One of the most effective and luxurious ways to relax is to enjoy the soothing comfort of a spa bath. Whether looking to relieve stress, soothe sore […]

We are very pleased to share that Ocean Future is actively participating in the Piscine Global Expo 2024, which is being held at the Versailles Exhibition Center in France from November 19th to 22rd, 2024. Our booth, located in 6F132, is currently experiencing a steady stream of visitors, and we have already felt the tremendous […]

Experience The Superior Quality And Design Of Modern Hot Tubs And Innovative Swim Spas At Piscine Global Expo 2024 The much-anticipated Piscine Global Expo will be opening in France and we will be exhibiting at it. The world’s most important bathtub exhibition will be the perfect stage to present our products to you. From 19th […]

Please Join Us On INTERNATIONAL POOL SPA PATIO EXPO 2024 Exhibition The INTERNATIONAL POOL SPA PATIO EXPO 2024 exhibition in UNITED STATES will be held on 12th-14th NOVEMBER, we will meet you there in Booth 8916. The customers are from all over the world. We are sincerely to invite you to come to visit us. […]

We are pleased to share the success of Ocean Future’s participation in the prestigious 28th Kitchen & Bath China 2024 exhibition, which took place from May 14th to 17th at the Shanghai New International Expo Centre. Our booth, located in Hall E6, Booth E12, attracted numerous visitors who were eager to explore our latest innovations in […]

The second phase of the 135th Canton Fair was successfully held from April 23 to 27, 2024. With the theme of “Quality Home Furnishing”, it concentrated on displaying 15 exhibition areas in three major sections: household products, gifts and decorations, and building materials and furniture. So Ocean Future seize this opportunity to bring our products […]


Ocean Future, the pioneering brand in wellness and relaxation solutions, has just unveiled its latest innovation in the realm of sauna experiences. Introducing the Ocean Future Infrared Sauna Rooms, a revolutionary addition to the world of home spas. Ocean Future Infrared Sauna Room has launched 11 new products this time, designed with the most advanced […]

This swim spa is equipped with a high-performance circulation filtration system, combined with advanced water flow regulation technology, to provide a uniform and stable water flow, suitable for swimming training, rehabilitation therapy, and relaxation. Multiple massage jets can accurately relax muscles, relieve fatigue, and bring immersive spa enjoyment. It uses a smart control panel to […]

This swim spa is equipped with a high-performance circulation filtration system, combined with advanced water flow regulation technology, to provide a uniform and stable water flow, suitable for swimming training, rehabilitation therapy, and relaxation. Multiple massage jets can accurately relax muscles, relieve fatigue, and bring immersive spa enjoyment. It uses a smart control panel to […]

The OF-2002 is designed with comfort and advanced features to enhance your spa experience. It includes a powerful LX pump and heater to ensure optimal water temperature and flow, allowing you to relax in comfortable water temperature and enjoy the unique experience of spa. This hot tub features 19 adjustable jets that provide full-body hydrotherapy […]

OFS12-2-T combines traditional sauna and infrared technology to provide users with a more comprehensive physical therapy experience. Traditional sauna stoves can quickly heat the entire space, bringing a deep sweating pleasure, while the infrared heating system can directly act on the human body, penetrate deep into the skin, and promote blood circulation and metabolism. This […]

This swimming pool spa uses advanced jet water technology to create a powerful and even endless swimming experience. The high-performance jet device can adjust the water flow speed to meet the needs of different swimmers, whether beginners or professional athletes, they can enjoy continuous swimming at home. It is also equipped with multiple hydromassage jets, […]

This sauna room is equipped with far-infrared heating panel, providing efficient and even heat distribution. It uses far-infrared technology to heat the body, penetrate deep muscles, help sweat and detoxify, promote blood circulation, and bring the ultimate relaxation experience. OFS02-2 is designed with a focus on modernity and functionality, and its exquisite appearance design can […]

PRODUCTS












 5800*3000*1500mm